Expert in Transgender Breast Augmentation

Dr. Steven Teitelbaum is an internationally renowned breast augmentation surgeon in Los Angeles and, for over two decades, has been helping transgender women in both first-time and revision breast enlargement. His goal with any gender-affirming breast augmentation is to provide natural, feminine, and beautiful breasts. Dr. Teitelbaum lectures at major plastic surgery meetings about the challenges unique to transgender breast enlargement, sometimes incorrectly referred to as “MTF top surgery in Los Angeles,” and teaches other plastic surgeons his technique to manage them.

Both cis and transgender women from around the world travel to Los Angeles to consult with Dr. Teitelbaum for breast augmentation. While he has been performing breast augmentation in transgender patients for over twenty years, he has seen an explosion of transgender patients over the past five years. He has operated on prominent and influential transgender women, including authors, activists, counselors, and celebrities. He and his office staff have the expertise and experience to help you in your journey.

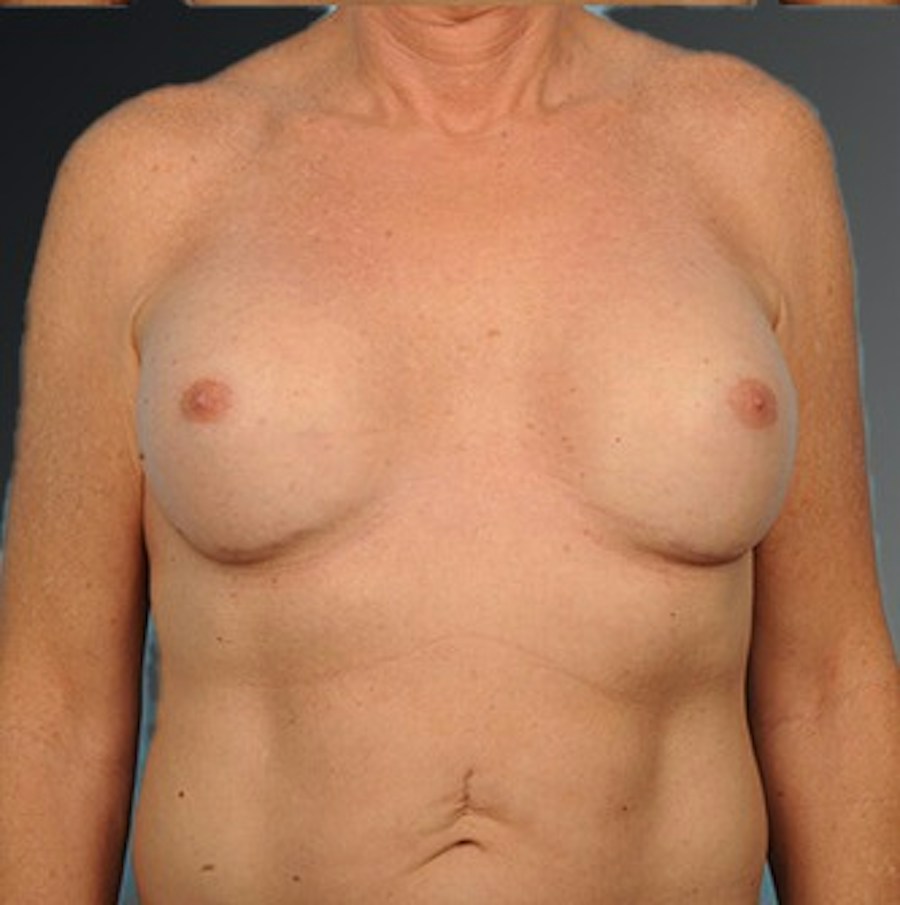
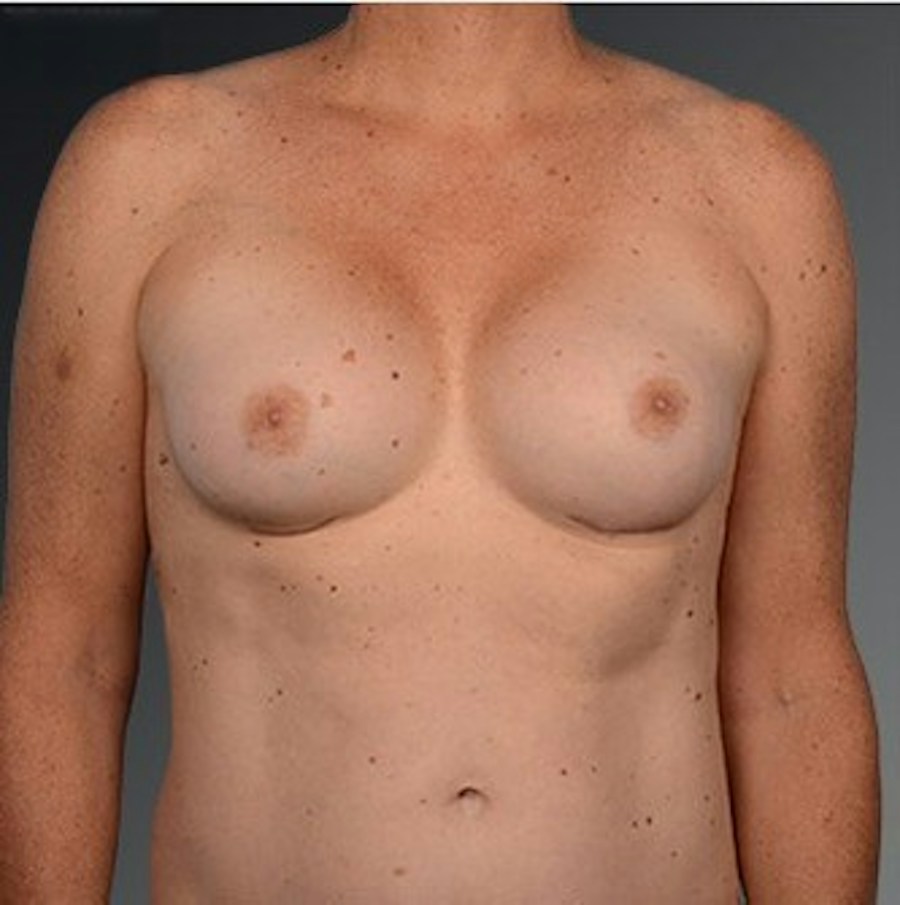
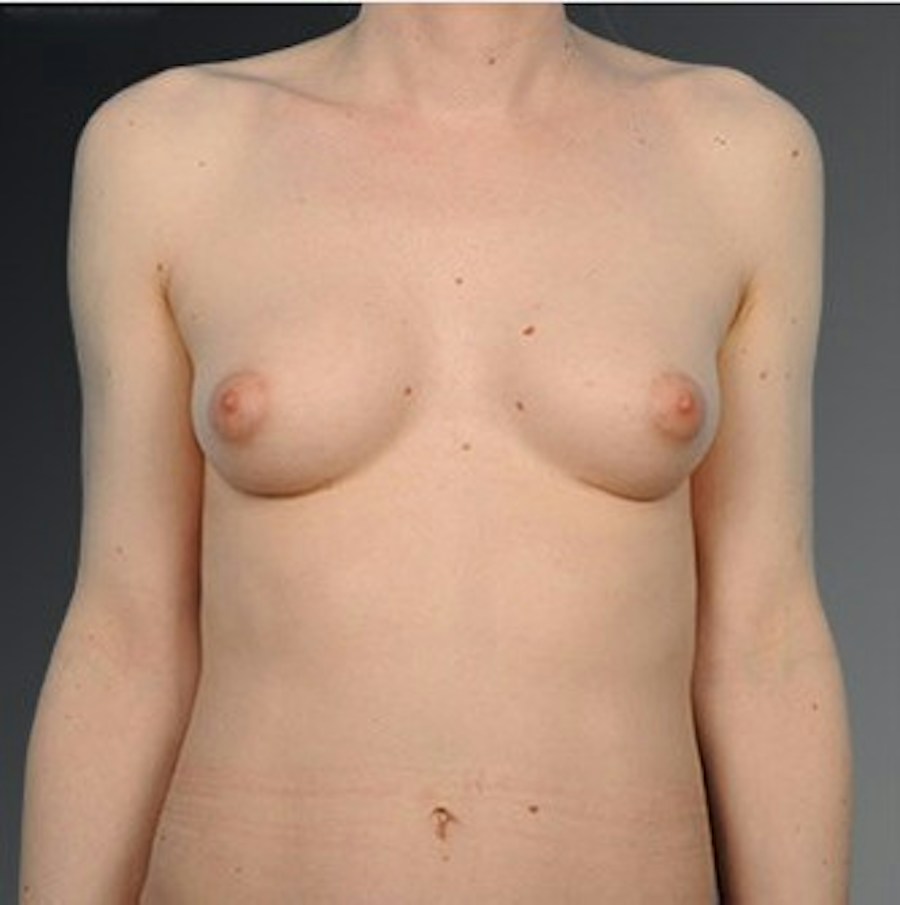
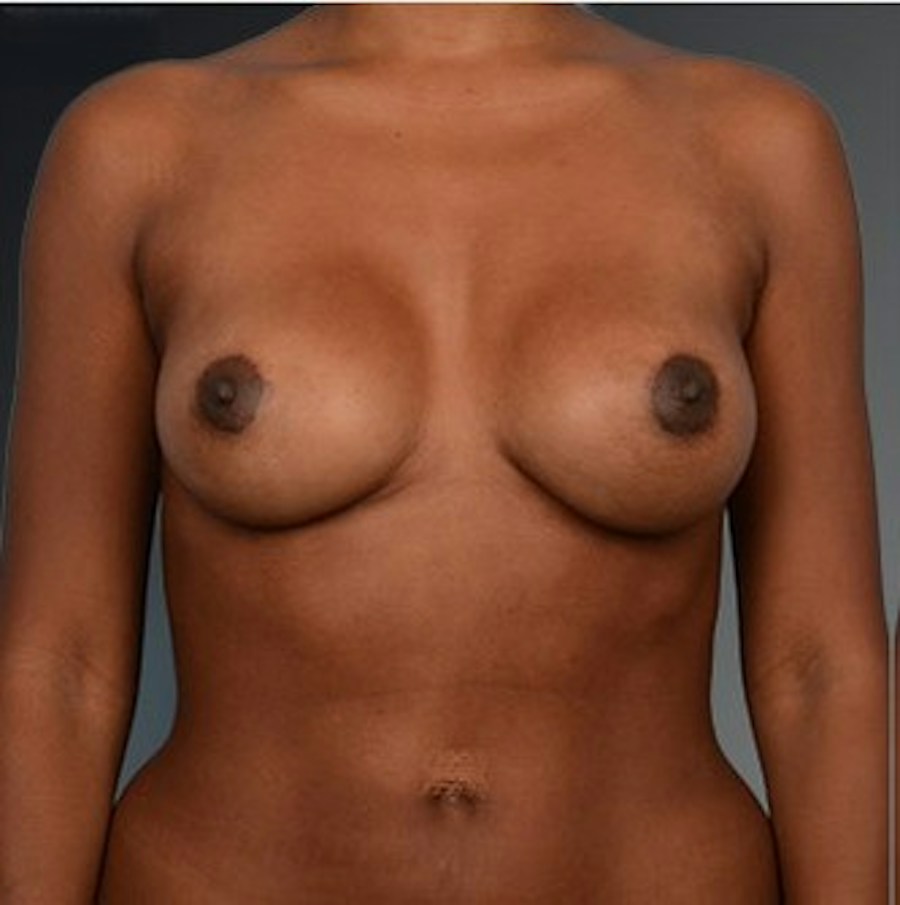
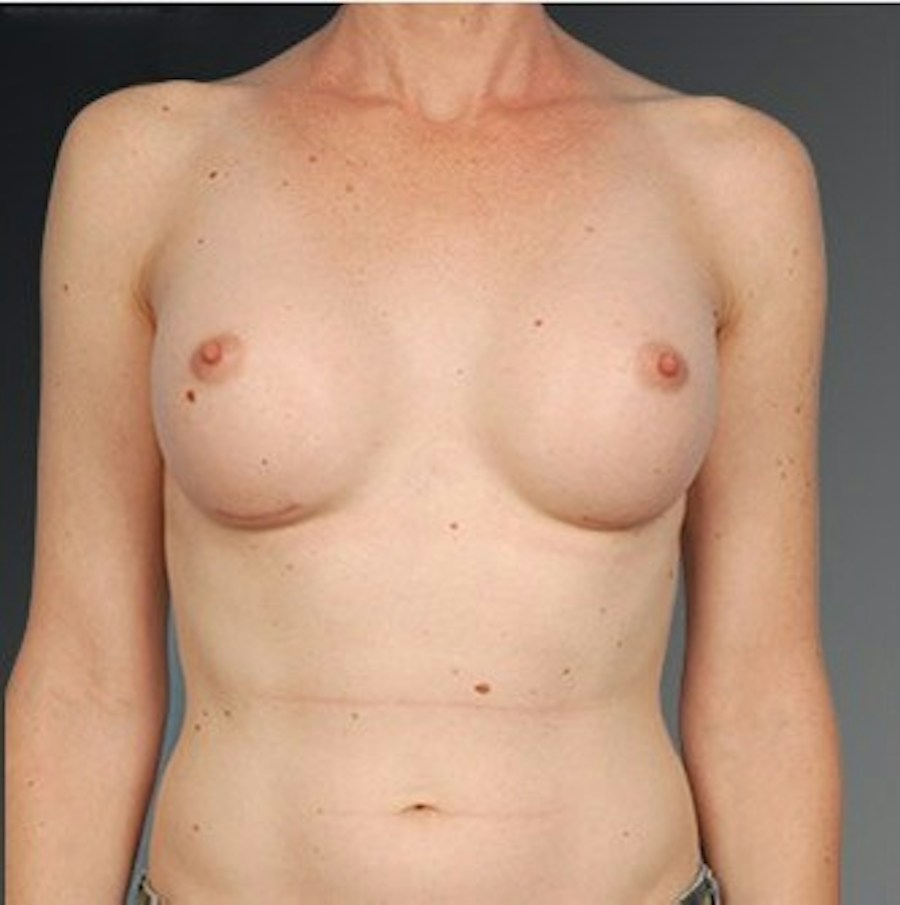
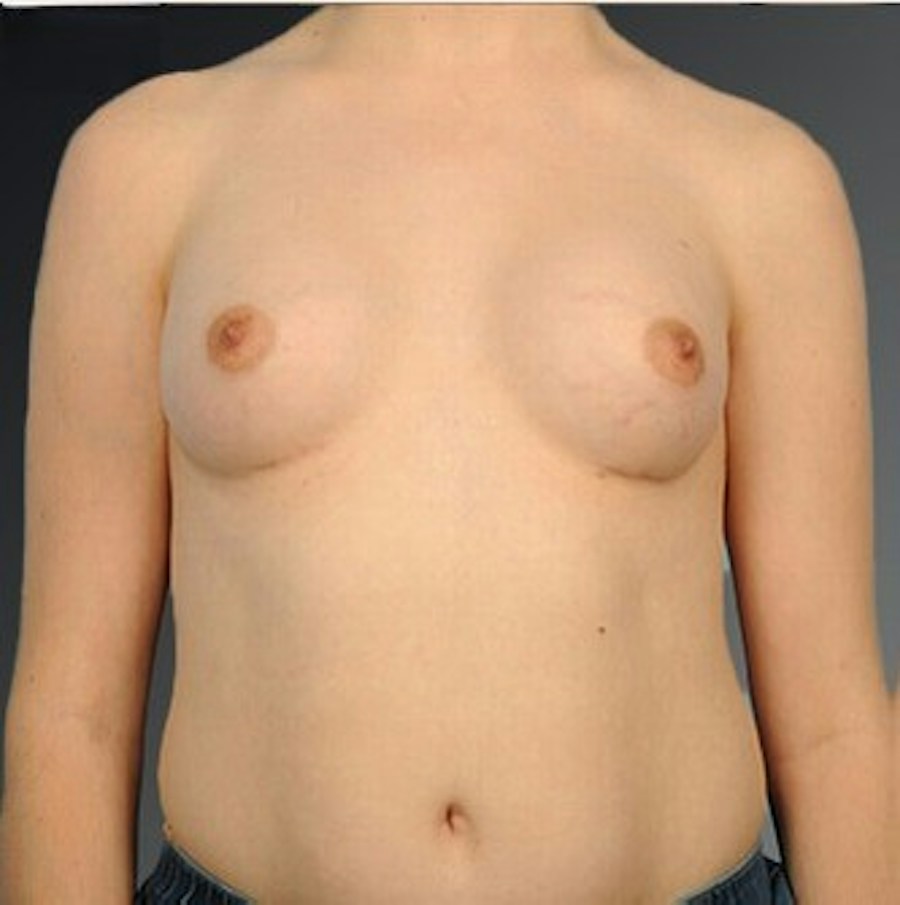
Before & After MTF Top Surgery/Transgender
Adult content

I am 18+ years old

Hub patient media

Adult content

I am 18+ years old

Hub patient media

Adult content

I am 18+ years old

Hub patient media

Adult content

I am 18+ years old

Hub patient media

Adult content

I am 18+ years old

Hub patient media

Adult content

I am 18+ years old

Hub patient media
Banner media

I’m so happy - we’re out for sushi, and the waitress just directed Leesa to the women’s bathroom, THANK YOU. We’re both almost in tears.

woman's nude body

Eager to Help Transgender Women

Dr. Teitelbaum has seen the increase of self-esteem and confidence in breast augmentation patients from teenagers who had correction of congenital deformities, to women who simply needed “a refill” after having babies. But there are few instances in which this increase in self-esteem is as profound as when he creates beautiful and feminine breasts for a transgender woman.

For trans patients, this is a major step beyond self-esteem: for many, breast enlargement is the defining moment in their transition. Gender identity may be on the inside, but it is undeniable that what we see on the outside affects both how we feel and how other people perceive us.


Cisgender v. Transgender Augmentation

At one level, the operations of a cisgender and transgender breast augmentation, often falsely referred to as “MTF breast augmentation,” are the same: an implant is being placed into a breast consisting of a nipple, skin, breast tissue, and muscle. The surgical instruments and fundamental anatomy are the same. However, there are profound differences in tissue dimensions and characteristics that require attention to specific details.

Both patient groups describe equally diverse goals. The requests of transgender patients are as varied as those of cisgender women, ranging from a subtle and natural change to a look that is disproportionate and obviously surgical. While Dr. Teitelbaum can make people look eye-catching and artificial, his niche is in the beautiful, graceful, and feminine. His patients most commonly ask for breasts that look natural, balanced, and proportionate; they usually specifically state that they do not want breasts that are overly large, round, bulging on top, or fake.

Schedule A Consultation

(310) 315-1121 Contact Us
Contact us media

Anatomical Nuances

There are at least seven important anatomic differences between cis and transgender augmentations that are too often unrecognized by patients and surgeons.

Rib Cage and Breasts

The rib cage and breasts of a trans woman are usually wider than those of a cis woman of similar height and weight. To create an ideal breast shape and ensure the breast fits the thorax, the surgeon must take multiple, precise measurements and select from a wide range of implants. While surgeons may just think of “volume” with a cisgender augmentation, looking independently at volume, height, width, and projection is important to creating beautiful breasts for the transgender patient.

Nipple Placement

A trans woman’s nipples are usually situated more to the outside of the breast mound. This affects where the implant should be placed so that the nipple ends up relatively centered (from left to right) on the breast mound.

Implant Position

A trans woman’s nipples are often situated low on the breast mound, affecting the final implant position. The ideal breast has about 55% of the breast volume below the plane of the nipple and 45% above. While sometimes the implant needs to be placed below the natural crease of the breast in a cisgender woman to achieve that balance, it is necessary far more often in the transgender patient.

Implant position is critical to the final result and must be planned exactly. Failure to properly determine where to situate the bottom of the breast and to keep the implant in that position are the two factors that account for most of the suboptimal results in transgender breast augmentation. Dr. Teitelbaum teaches other surgeons a specific technique to manage this issue.

Tissue Texture

All breasts are made up of a combination of fat (soft) and glands (firm). Breasts in transgender patients are firmer and denser because, unless they are significantly overweight, their breasts are predominantly made up of glands that are enlarged from the hormone therapy. They are often akin to the breasts of a cisgender woman during puberty, typically lacking the fatty component to their breasts that gives breasts their natural sway and squishiness.

Since most patients want to have youthful and perky breasts, this is typically not a problem. But it is important for surgeons to take the reduced malleability of breast tissue into account, as this affects implant sizing, and it is important that prospective patients understand what this might mean for their results.

Skin Quality.

Transgender patients often have thicker, tighter skin. Years of fluctuating breast size from monthly periods, weight changes, gravity, and genetically thinner skin can further thin the skin. A transgender patient usually has their augmentation sooner after the beginning of their hormone-induced female “puberty” than a cisgender woman might, so the skin has been more recently stretched, and it has not had the chance to relax and soften.

Breast Position

The combination of the denser tissue and less compliant skin yields a breast that is thicker, tighter, and higher than that of the typical cisgender patient. This is important to understand because it means that the breasts usually end up very high, perky, full, firm, and tight, yet at the same time, many prefer breasts that are a little lower, less full, and with more “bounce.” Dr. Teitelbaum carefully explains to each patient the range of possibilities available so she can choose.

Pectoralis Major Muscle

The pectoralis major muscle is often (but not always) thicker in a transgender woman. Rarely is it thick enough to pose a problem; it just requires greater attention to anesthetic and technical considerations during surgery. There may be a greater tendency for the muscle to push the implants slightly down and out over time, though this is also an issue for cisgender patients.

Dr. Teitelbaum’s Unique Approach

The goal of gender affirming breast surgery (MTF top surgery is a common misnomer) is to create beautiful, natural-looking breasts. Dr. Teitelbaum employs an innovative surgical technique that makes such breast augmentations more beautiful and predictable. It takes into consideration the concerns mentioned above and aims to avoid the pitfalls. These improvements are:

  • Meticulous and detailed assessment of anatomy
  • Understanding exactly what each patient wants, rather than allowing Dr. Teitelbaum’s own aesthetic to determine the result
  • Suggesting an implant size and dimensions that best change your shape into the one you want
  • Using a computer simulation to demonstrate what to expect
  • Using absorbable mesh during surgery to “fix” the inframammary fold (the bottom of the breast) into an exact position on the chest wall in order to create a crisp and accurate bottom of the breasts
  • Often use anatomically shaped implants to better control the balance of breast fill
  • Using the same meticulous surgical technique, nerve blocks, and rapid recovery, he has used with thousands of cisgender patients

This approach creates a more natural and beautiful breast appearance, with an ideal amount of volume above versus below the nipple, nice expansion and fill of the lower pole, and an upper pole that feathers out and transitions gradually into the upper chest. Dr. Teitelbaum has presented this technique to many plastic surgery organizations, including the 2018 Atlanta Breast Symposium: the largest plastic surgery meeting in the world, focused strictly upon breast surgeries. He has been invited to write a book chapter on transgender breast augmentation for an upcoming major textbook of breast surgery. 

Banner media
womans neck and shoulders

A Kind and Respectful Office

Dr. Teitelbaum and his staff take great pride in helping trans women realize their authentic selves. He and his staff are pleased to help patients who are transitioning, and are sensitive to their unique fears, concerns, hopes, and dreams.

Some patients seek a very natural and feminine augmentation – as if they had naturally moved through female puberty. Others desire breasts that garner attention. Whichever you prefer, Dr. Teitelbaum can make them beautiful. You will find everyone you speak to, on the phone and in person, dedicated to your personalized care and a comfortable recovery.

Fat Injection for Transgender Breast Augmentation

Many trans patients ask for liposuction of their love handles to enhance a feminine, hourglass figure. Sometimes this fat is transferred to the buttocks or the outer thighs. This fat can also be used for the breast. Fat alone does not produce a breast of adequate size, but it can help widen a breast that has responded very well to hormones. It can also be used in conjunction with an implant to conceal the implant edges and make the breast look more natural than it might with an implant alone.

Why Choose Dr. Teitelbaum for Transgender Breast Augmentation?

Trained in surgery at Harvard, Dr. Teitelbaum is one of the most respected plastic surgeons in the world. He is one of the most sought-after lecturers on breast augmentation worldwide, and his contributions to the field are significant. Though his office is located in the Los Angeles area, his patients come from around the world. He has achieved a reputation for surgical excellence, based upon his outstanding skills, including when performing gender affirming breast augmentation. As reported in Allure, “he produces astonishingly natural results.”

Dr. Teitelbaum is an Associate Clinical Professor of Plastic Surgery at UCLA School of Medicine (Advanced Level Resident Instructor), and a widely sought speaker, educator, patient advocate, and innovator. His interest in transgender breast augmentation in Los Angeles spans two decades, and he is responsible for developing a superior, cutting-edge surgical technique.

Doctor media

Your Confidential Consultation

Ahead of your procedure, you’ll join Dr. Teitelbaum for a private, one-on-one consultation at his Los Angeles office. There, you’ll discuss your aesthetic goals and medical history, and he’ll perform a physical examination to ensure your breast tissue is healthy and ready for an augmentation.

MTF Top Surgery FAQs

Is gender affirming breast augmentation surgery tax-deductible?

This is something to always ask your accountant. Click here to view a 2016 article from the Huffington Post about this topic.

How old do you have to be to have a breast augmentation?

Saline implants are FDA approved for women 18 and over, and silicone implants are approved for women 22 and over. They can only be used in younger women for reconstructive surgery. In fact, the younger a woman transitions, the shorter the period of time of male hormones, the better the result. In these situations, Dr. Teitelbaum will confer with your therapist and general physician.

Is hormone therapy required?

You should be on hormones for a minimum of one year, and your breast development should have stabilized. He has performed breast augmentation on people who have been on hormones for less than a year, but in those cases has spoken with their personal physician.

Is a note from a therapist or a set number of counseling sessions required?

Breast augmentation does not require a note from a therapist or special counseling; all that is required is hormonal therapy and the patient's commitment. What is important is that a patient understands the risks and benefits of surgery, has a support system, and has thoroughly considered all of the issues.

Will insurance cover gender affirming breast augmentation?

This is still in flux and varies by state. Dr. Teitelbaum is not an insurance provider and is not on any network. His fee remains the same and is paid by each patient. If there is an opportunity for insurance reimbursement, the patient is responsible for filing the claim, but Dr. Teitelbaum’s office will assist you in any way it can.

Should breast augmentation occur before FFS or GRS?

While breast augmentation surgery usually occurs before facial feminization surgery (FFS) and gender reassignment surgery (GRS), it may occur after. This is a personal choice for each patient. It is affected by the degree of breast development under hormonal influence and the priorities of the individual patient.

How much pain is there after surgery?

Dr. Teitelbaum has been teaching a 24-hour recovery after breast augmentation for many years, and is as successful at doing this in both trans and cis women. It is the result of complete preoperative planning, a detailed understanding of anatomy, gentle and precise surgical technique, and an excellent anesthesiologist.

Does a person have to identify as a female to receive a breast augmentation, or can non-binary individuals receive a breast augmentation?

There are no rules or laws governing this. Dr. Teitelbaum assesses each patient individually. Usually, he does not need to speak with a patient’s therapist, but on a case-by-case basis, he may feel that it is best.

Is there a limit to how large a person’s breasts can be enlarged?

If the patient wants to look natural, then there is a limit. If a breast has too small an implant, it will be empty. If the implant is too big, the breast will look stuffed. His measurement system and computer simulation will help you to see this.

What is the role of fat grafting?

Fat grafting can enlarge breasts that have reached their full size with hormones, but it does not make a significant difference in size. However, when tissue coverage is thin, fat grafting to the breast smooths the edges and helps conceal the implants.

Which incision does Dr. Teitelbaum suggest?

The inframammary (IMF) or under the breast incisions is today’s most often used approach for both cis and transgender augmentation. The scar is the most concealed, but most important of all is that study after study has shown a reduced incidence of a large number of complications after breast augmentation, and an overall reduced rate of revision surgery.

Are implants best placed in front of or behind the muscle?

For both cisgender and transgender women, the implant is typically placed behind the muscle. This is because the more tissues there are over the implant, the more the edges are obscured and the more natural it appears. It also has a lower rate of capsular contracture, a buildup of thick scar tissue around the implant.

However, when the implant is behind the muscle, it can move with the pectoralis muscle, and there may be an increased tendency for outward migration over time. While Dr. Teitelbaum and most plastic surgeons place the implant behind the muscle in most cases, there are circumstances in which it is appropriate to place it in front of the muscle.

What is the unique thing that Dr. Teitelbaum does differently than most other surgeons with transgender breast augmentations?

The key difference is the firm fixation of the breast base to the chest wall. This should be highly defined. He does it with an absorbable mesh, and it makes a big difference. It is not a requirement that you do it this way, and in some trans patients, the crease is already at the right place and is well defined.

What type of implant does he use?

Dr. Teitelbaum has used and continues to use every type of implant that is available in the United States, including saline and silicone, gummy bear, round and teardrop, smooth and textured. There is a particular role for teardrop implants in transgender patients, and he will explain those to you at your consultation, along with the tradeoffs of using them.

What can be done to enlarge nipples?

Nipples in transgender women are usually narrower and shorter than those of cisgender women. While there are reconstructive techniques to make nipples that have been lost from a mastectomy, these are not fine enough to be used simply to enlarge a nipple.

Can my areola be made larger?

The darkly pigmented areola skin cannot literally be made larger. But tattooing can be done to make them larger or darker.

Are there risks that are more common with transgender breast augmentation?

The only problem that seems to be more common with breast augmentation in trans women is implant malposition, specifically meaning that the implant slides down and is too low in the body. This can require a revision. That is why Dr. Teitelbaum emphasizes the benefits of using an absorbable mesh to secure the implant in position.

What happens to nipple sensation?

There is always a risk of partial or complete loss of nipple sensation from a breast augmentation, in both trans and cis women. That risk is less than 10%, but that is, of course, very significant to those who want to maintain it.

How does HRT affect breast cancer risk?

Dr. Teitelbaum has spoken with endocrinologists and breast cancer surgeons, and no one has a clear answer to this question. As more and more women live out the rest of their lives after decades of hormones, we will know better.

While mastectomy is usually not recommended for patients with the BRCA 1 and BRCA 2 breast cancer genes, including male breast cancer, it is important to understand how hormonal therapy will affect these patients’ breast cancer risk. When Dr. Teitelbaum sees a woman on hormones for a breast augmentation with a significant family history of breast cancer, he always refers them to a breast cancer specialist or geneticist.

Should transgender women with breast implants get mammograms?

This has not generally been recommended in the past. It is also problematic because the breasts of trans women are typically so dense that the mammogram would look very cloudy, with little visualization of the breast. However, women with particular family histories or genetic predispositions may need to consider it on a specific basis.


References

Accessibility: If you are vision-impaired or have some other impairment covered by the Americans with Disabilities Act or a similar law, and you wish to discuss potential accommodations related to using this website, please contact our Accessibility Manager at (310) 315-1121.
Contact Us